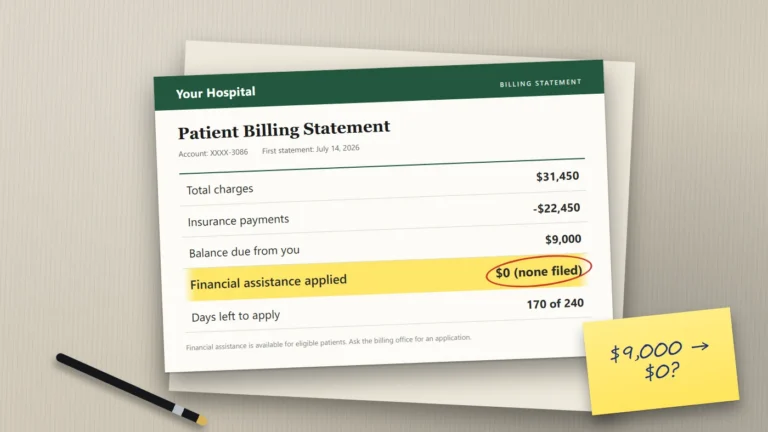
Picture a statement of the kind hospitals mail out every day. The numbers here are made up, but the format isn't: "Hospital services: $14,260. Insurance adjustments and payments: $11,080. Amount you owe: $3,180." Below that sit a due date and a tear-off payment slip.
So what are you supposed to check? Three totals and a deadline. You can't tell whether you were charged for two nights or three. You can't tell whether the scan that got canceled still landed on your account, or whether your insurer was even billed under the right member number.
For that you need the long version, which hospitals call an itemized bill or itemized statement. Once it's in your hands, the guessing stops. Every charge gets its own line, so that canceled scan either shows up with a date of service and a price next to it, or it doesn't. Next to each price you'll see the billing code the hospital used, a few words about what the charge was for, and how many units it counted. A quick ER visit might fit on half a page. Surgery with a hospital stay often runs several pages.
Most hospitals won't mail it unless you ask. So ask. You don't need a lawyer or a special form. A phone call usually does it, a short letter if the call goes nowhere, and federal law is on your side either way.
How often are hospital bills wrong?
There's a number that floats around online: 80% of medical bills contain errors. Trace it back, though, and you end up at companies that sell bill-review services, not at an audit anyone can inspect. We looked for a credible national study behind it and didn't find one, so we won't pass it along as fact.
That doesn't mean your bill is clean.
Think about who ends up fighting a medical debt collector. When people with Medicare complained to the Consumer Financial Protection Bureau about one between 2020 and 2022, more than half said the debt itself was inaccurate. The exact share was 53%. For people with a second layer of coverage, say Medicare plus a supplement, it went up to 61%. Makes sense: each extra insurer adds a handoff between billers, and handoffs are where things slip.
53%. In more than half of the medical debt collection complaints the CFPB received from people with Medicare between 2020 and 2022, the person said the bill was inaccurate.
Doubt alone keeps plenty of bills sitting unpaid. The same CFPB report cites a 2022 survey where 44% of adults said they hadn't paid a medical bill in full because they weren't sure it was accurate.
What about claims somebody actually audits? Medicare checks a sample of its own fee-for-service claims every year. For fiscal year 2025, the Centers for Medicare & Medicaid Services estimated that 6.55% of those payments were improper, or about $28.83 billion. Mostly it's paperwork: missing or insufficient documentation, plus coding problems. The count also includes underpayments, not just overpayments. None of that proves your bill is wrong. It does show that billing mistakes are routine, even on claims the government reviews.
And no, the hospital probably isn't out to cheat you. A single stay can generate hundreds of charge entries, keyed in by different departments at different hours by people who never see the whole account. Errors are exactly what you'd expect from a setup like that, and the itemized bill is how you find them.
Your right to the billing records
You may hear that hospitals "must give you an itemized bill." Close, but not quite, and the difference matters if a billing clerk pushes back.
Your leverage comes from HIPAA, the federal privacy law. It lets you see and get a copy of your records in what the rule calls the designated record set. That phrase sounds like lawyer talk until you read how the regulation defines it for a health care provider: your medical records and your billing records. The line-by-line charges? Billing records. They're yours to see.
How long can the hospital sit on your request? Generally 30 calendar days. If it needs more time, it gets one extension of up to 30 more days, and it has to tell you why in writing. It's allowed to insist that you ask in writing, and it can charge a reasonable, cost-based fee for copies. An unpaid balance, though, isn't a reason it can use to turn you down, according to HHS guidance.
You'll rarely have to quote any of this. HIPAA never uses the words "itemized bill" and doesn't dictate a format; what it guarantees is access to the underlying records. Nearly every hospital billing system can print an itemized statement in minutes, and most billing offices will do it on a plain phone request. Nobody has to bring up the regulation number or the word HIPAA.
Live in Texas? You've got more. Since September 1, 2023, a provider that wants payment from a patient has to send a written itemized bill first, with a plain-language description of each service or supply, the billing codes sent to the insurer, and the amount due for each one. Until it does that, it can't pursue debt collection. Other states have their own rules, and they differ, so your state attorney general or insurance department is the place to ask.
Getting the document is the easy part. Reading it is where the money is, and that goes faster when you know which handful of errors keep turning up.
How to request it
- Call the billing number on the statement. Say: "I'd like an itemized statement for account number ___, for dates of service ___, showing the revenue codes, the CPT or HCPCS codes, the quantity and the charge for each line." Ask how it'll be sent and when.
- Ask them to hold the account. Request that the account be put on hold and kept out of collections while you review the charges. Write down the date, the person's name and what they agreed to.
- Put it in writing if nothing shows up in two weeks. Send a short letter or portal message asking for a copy of your billing records under the HIPAA right of access, 45 CFR 164.524. Keep a copy. The 30-day clock starts when they receive it.
- Get the insurer's version. Download the explanation of benefits for the same dates from your health plan. On Medicare, pull the Medicare Summary Notice or check your online Medicare account. Put it next to the hospital's bill and you'll see what was billed, what the plan allowed and paid, and the most the hospital can charge you.
- For a big bill, request the medical record too. The same HIPAA right covers it. With the discharge summary, the medication list and the operative report in hand, you can confirm what was actually done, and for how long.
Which errors are worth hunting for?
You're not auditing the hospital's coding. You're checking facts you know better than anyone: when you arrived, when you left, what was done and what got called off.
| What to check | What an error looks like | What to compare it with |
|---|
| Duplicate lines | The same test, drug or supply on the same date twice | Your memory, the medical record |
| Dates and room days | A room charge for the day you went home, or for a day before you arrived | Admission and discharge times |
| Quantities | 10 units of a drug when you got 1; four hours of recovery room for a 40-minute stay | Medication list, nursing notes |
| Canceled services | A scan, lab or consult that was ordered and then called off | Your memory, the record |
| Time-based charges | Operating room or anesthesia minutes far above what the operative report shows | Operative and anesthesia records |
| Routine items billed separately | Gloves, gowns and basic supplies as their own lines | Ask whether these belong in the room rate |
| Insurance details | Wrong member ID, wrong plan, no insurer payment posted | Your insurance card and the explanation of benefits |
| Balance above the allowed amount | You're billed more than the "patient responsibility" on the insurer's notice | Explanation of benefits or Medicare Summary Notice |
| Out-of-network line at an in-network hospital | A separate out-of-network charge for emergency care, anesthesia, radiology or pathology | No Surprises Act protections |
Two more checks take a few minutes.
Emergency visits are billed at levels, usually 1 through 5, and the higher the level, the higher the price. Were you in and out with a simple problem, yet the visit's coded at the top level? You're allowed to ask what supported that. You may not win the argument. It's still a fair question.
Then look up the hospital's own prices. Federal rules have required hospitals to post their standard charges online since January 1, 2021, and that includes a consumer-friendly list of at least 300 services you can schedule ahead of time. If a line on your bill is far off the posted figure for the same code, ask why.
How to dispute what you find
Mark each line you question and send the billing office a short written dispute listing the line, the date, the amount and the reason, something like: "Line 14, CT scan, March 3, $2,140. This scan was canceled and not performed." Ask for a corrected statement. If insurance was involved, ask them to send a corrected claim to the insurer, because your share is calculated from the claim.
Sometimes the hospital billed correctly and the plan processed the claim wrong. That's a job for the plan's appeal process: you can file an internal appeal and, if that fails, ask for an external review by an independent party.
Uninsured, or paying on your own without insurance? Before scheduled care, you should've gotten a good faith estimate. Hang on to it. If the provider's final bill comes in at least $400 above that estimate, federal rules let you start a patient-provider dispute, as long as you do it within 120 days of the bill. There's a $25 administrative fee. The No Surprises Help Desk at 1-800-985-3059 can walk you through filing.
Already in collections? Then dispute it in writing with the collector as well, within 30 days of its first notice, so it has to verify the debt. The CFPB takes complaints about medical billing and collections at (855) 411-2372. So does your state attorney general.
When outside help is worth paying for
A careful person can review a modest bill alone. Some cases are harder: a stay with pages and pages of charges, several doctors billing separately, two insurers pointing at each other, or a billing office that just stops answering.
That's when people bring in a medical billing advocate. A good one reads the itemized bill and the records, finds coding and coverage problems, files the disputes and appeals, and negotiates whatever's left. Fee models differ; some charge by the hour and some take a percentage of what they save you. Get the fee in writing, ask what happens if they save nothing, and compare two or three before you sign. Many states also run free consumer assistance programs for insurance problems, and a hospital's own financial counselors can tell you if you qualify under its financial assistance policy.
Is a correct bill the end of it? Not always. Hospitals routinely accept less than the listed charge from insurers, and many will talk about a prompt-pay discount or an interest-free payment plan with patients who bother to ask.
And if the review shows that most of your balance is simply your deductible, the fix for next year sits on the insurance side. Open enrollment for 2027 marketplace coverage starts November 1. Medicare's fall enrollment runs October 15 through December 7. When you compare health insurance quotes, look at the deductible, the out-of-pocket maximum and whether your hospital is in the network, not just the premium.
Mistakes to avoid while you wait
Paying first and checking later. Refunds happen, but slowly. A disputed charge is easier to remove than to claw back.
Putting the balance on a credit card. That turns a hospital account you can dispute into card debt that runs up interest.
Going silent. A dispute doesn't stop the billing cycle by itself. Keep your requests in writing, keep copies, and open the hospital's mail.
Treating it as an accusation. Most errors are clerical. "Can you help me understand this line?" gets further with a billing office than "you overcharged me."
My advice: ask for the itemized bill before you pay anything on a hospital account of any size. If every line checks out, you've lost a week. If one doesn't, you've caught it while the account is still open and the hospital still has a reason to fix it.
This article is general information, not financial, legal, tax or medical advice.